
A Policy Change With Real Human Costs
For years, a pain physician’s patient lived with chronic pelvic pain she described as a hot poker. A targeted nerve block eliminated that pain entirely. Through tears, the patient said she had forgotten what life without pain felt like. Beginning in late October, new Medicare policies will make that kind of relief inaccessible to millions of patients just like her.
Five regional Medicare Administrative Contractors — private companies that apply Medicare rules across 37 states and several U.S. territories — have finalized policies restricting coverage for a wide range of peripheral nerve procedures used to diagnose and treat chronic pain. The author of this analysis, Dr. Antje M. Barreveld, is chief of pain medicine at Newton-Wellesley Hospital and immediate past president of the American Academy of Pain Medicine.
The new restrictions arrive despite sustained pushback from patients, physicians, and advocates, and despite the fact that these procedures have been standard tools in pain care for decades. The final policy is marginally less severe than the version proposed earlier in 2025, but it still strips coverage for procedures targeting nerves including the pudendal nerve and ganglion impar — interventions used specifically for severe pelvic pain conditions that leave patients unable to sit, dress, or move through a day without agony.
What Peripheral Nerve Blocks Actually Do
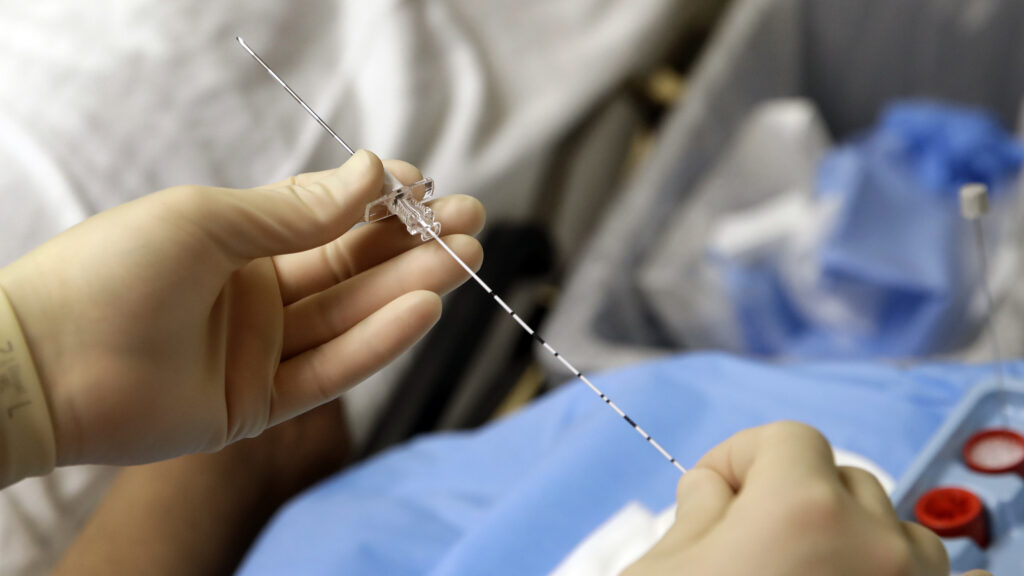
A peripheral nerve block delivers numbing medication directly around a nerve, interrupting pain signals at their source. The immediate effect lasts only a few hours, but for many patients, relief extends well beyond that window — sometimes for weeks or months. These procedures also serve a diagnostic function, helping clinicians identify exactly which nerve is generating a patient’s pain.
Critically, nerve blocks do not exist in isolation. They function as one component of multimodal pain care, enabling patients to engage in physical therapy, reduce their reliance on medications, avoid emergency room visits, and sometimes delay or avoid surgery entirely. Stripping coverage for these procedures does not make chronic pain disappear; it forecloses one of the most targeted, least invasive options available.
The Evidence Question — and Why It Is More Complicated Than It Looks
The Medicare contractors who drafted these restrictions point to genuine limitations in the research: small study populations, short follow-up periods, and uncertainty about whether benefits persist. These are not invented concerns, and the contractors have a legitimate oversight role in identifying where evidence is weak.
But chronic pain presents a structural problem for conventional evidence gathering. Pain is inherently subjective, and it varies profoundly from one patient to the next. A treatment that produces only modest average benefit across a study population may deliver life-altering relief to a specific individual. Population-level data is essential, but it cannot always identify which patients will experience clinically meaningful improvement — and for the roughly one in four U.S. adults living with unrelenting chronic pain, even a sustained reduction in suffering can restore basic function and dignity.
The absence of perfect evidence is not the same as evidence of absence. What the evidence gaps actually demand is more federal investment in larger, longer-term studies — not immediate coverage cuts that remove the very treatments researchers need to study in real-world conditions.
The Opioid Crisis Lesson Medicare Seems to Be Forgetting
One of the hardest-won lessons of the opioid epidemic is that people with chronic pain need access to a broad range of non-opioid alternatives. Restricting peripheral nerve procedures does not reduce the underlying burden of pain — it redirects patients toward fewer options, and in some cases toward the opioid pathways that public health policy has spent years trying to reduce.
Dr. Barreveld describes patients who arrived in her clinic after being passed from specialist to specialist, never receiving an adequate explanation of their condition or a treatment that worked. An 87-year-old with severe bladder pain told her, “I see it in their eyes — they don’t know what to do with me.” For patients like her, a nerve block was not a luxury or an experimental gamble; it was the first effective intervention anyone had offered.
It is fair to ask whether some of these procedures are overused, or whether financial incentives shape their application. Medicare should not fund treatments indefinitely when they demonstrably fail to help. But the answer to those legitimate concerns is rigorous, well-funded research combined with carefully calibrated coverage standards — not blanket restrictions that deny access before better evidence even exists.
Who Bears the Cost of This Decision
The patients most exposed by these new policies are not wealthy. Individualized pain care should not depend on private insurance coverage, personal connections, or financial resources. When Medicare restricts access to a treatment, it does not restrict it equally — it restricts it most severely for the patients who have no other way to pay.
As these policies take effect, Medicare contractors must commit to revisiting restrictions as new evidence emerges. Researchers, clinicians, and specialty societies must simultaneously build the larger, longer-term studies that regulators say they need to justify broader coverage. Coverage standards must be designed to recognize clinically meaningful benefit, not just statistically clean trial results. The tools physicians use to relieve suffering must remain within reach of the patients who need them most.